Best practices for agentic population health and value-based care data: a field guide for population health and value-based care data teams
How population health and value-based care data teams move their data back office to agents, practice by practice: the state of the space, the old world and the new, what the agents do step by step, how to set autonomy, who owns what, and how to start.
Value-based contracts pay for outcomes that depend on late, changing data.
Making payer data usable is repeatable work for agents.
The state of the space
Teams that run attribution, registries, risk scores, quality gaps and contract performance for value-based arrangements. They combine EHR data with payer claims files, attribution lists and social data, and serve care management, finance and contracting.
Value-based contracts pay for outcomes, but the data to manage them arrives late from payers in formats that change every month. Teams spend most of their time making files usable. Agents can land, map and reconcile payer data continuously, so care teams act on current lists and contract performance is visible before settlement.
The old world
A payer changes its file layout; attribution stops for a month; care gaps go stale.
It is rarely one failure. Three patterns repeat:
- •A payer file in a new layout. A payer changes its claims file; attribution and cost reports stop for a month.
- •Care gaps closed in time. Gap lists are a month old when care managers get them.
- •Contract performance before settlement. Shared savings are a surprise a year later.
The new world
The layout was mapped on arrival and registries kept refreshing.
Here is that new world as a chain of hand-offs between agents:
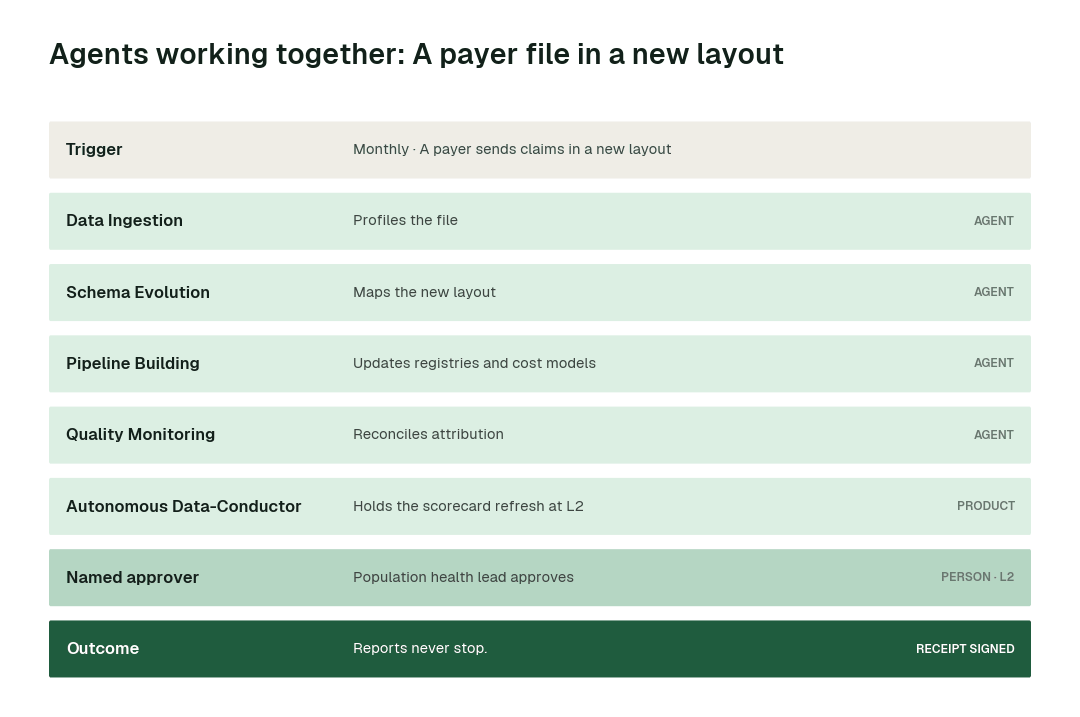
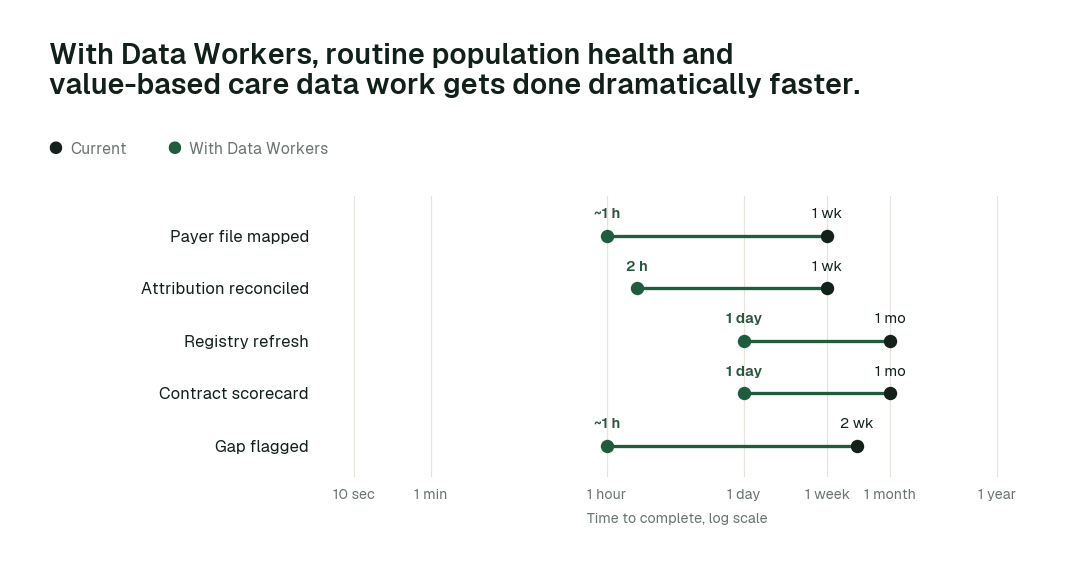
These are the impact metrics we move:
- •Gap flagged: from about 2 weeks to ~1 h
- •Payer file mapped: from about a week to ~1 h
- •Attribution reconciled: from about a week to 2 h
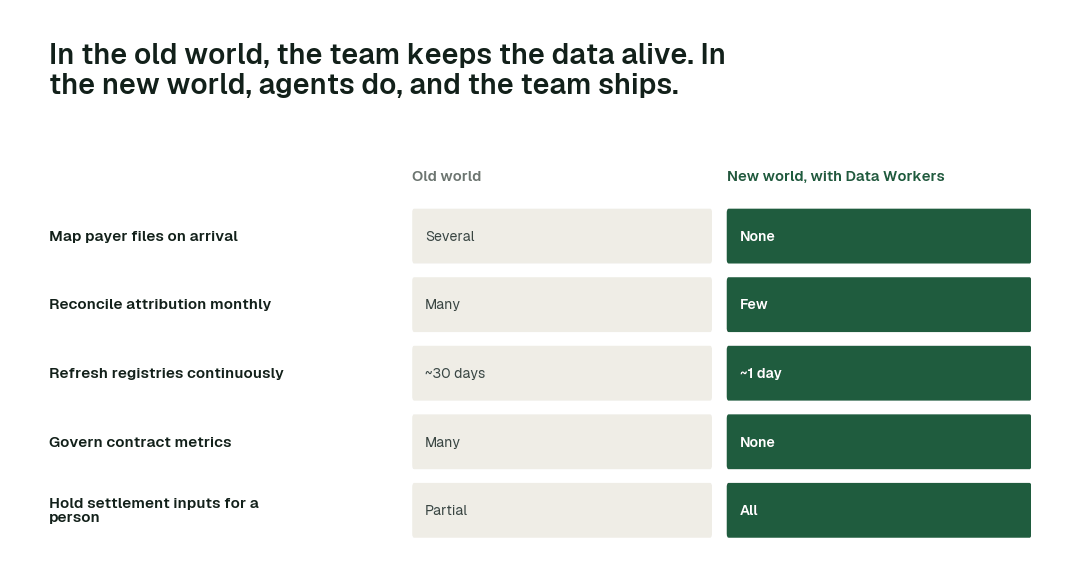
The rest of this report walks through the 5 practices that make that possible. At a glance:
The practices, one by one
1. Map payer files on arrival
Layouts change monthly.
Why it is harder than it looks. Every payer changes formats on its own schedule.
The old world. Manual mapping.
The new world. Schema Evolution.
What the agents do, step by step:
- 1.The Data Ingestion agent calls
get_connector_statusand profiles files.
- 1.The Schema Evolution agent calls
generate_migrationand maps layouts.
- 1.The Pipeline Building agent calls
sandbox_testand tests models.
In practice. No lost months.
What to measure. Months without reports.
2. Reconcile attribution monthly
Disputed panels cost money.
Why it is harder than it looks. Attribution sources disagree.
The old world. Disputes.
The new world. Quality Monitoring.
What the agents do, step by step:
- 1.The Quality Monitoring agent calls
run_quality_checkand reconciles attribution.
- 1.The Incident Debugging agent calls
get_root_causeand explains differences.
- 1.The Autonomous Data-Conductor calls
request_governance_reviewand routes disputes.
In practice. Agreed panels.
What to measure. Attribution disputes.
Practices like these compound. Across the routine work they cover:
3. Refresh registries continuously
Care needs current lists.
Why it is harder than it looks. Registries depend on many feeds.
The old world. Monthly rebuilds.
The new world. Pipeline Building.
What the agents do, step by step:
- 1.The Pipeline Building agent calls
generate_pipelineand maintains registries.
- 1.The Quality Monitoring agent calls
set_slaand keeps feeds fresh.
- 1.The Data Security agent calls
scan_piiand classifies PHI.
In practice. Current lists.
What to measure. List age.
4. Govern contract metrics
Leaders need one number.
Why it is harder than it looks. Contract terms define metrics differently.
The old world. Many.
The new world. Context Wizard.
What the agents do, step by step:
- 1.The Data Context & Catalog agent calls
define_business_ruleand governs metrics.
- 1.The Data Context & Catalog agent calls
trace_cross_platform_lineageand adds lineage.
- 1.The Data Context & Catalog agent calls
generate_documentationand documents terms.
In practice. One number.
What to measure. Conflicting metrics.
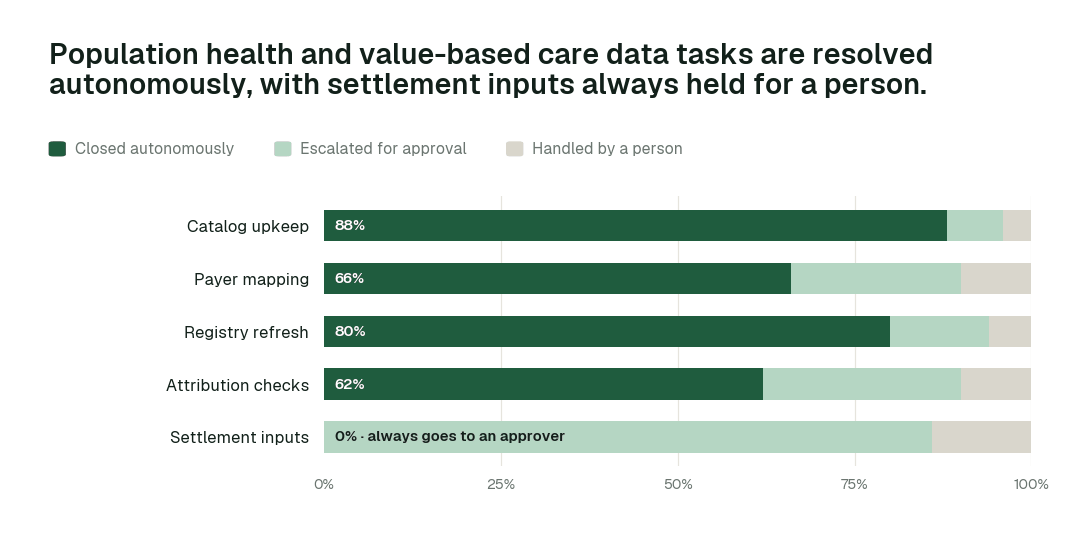
Autonomy where work is reversible, a named approver where it matters:
5. Hold settlement inputs for a person
Money moves.
Why it is harder than it looks. Settlement moves money.
The old world. Mixed.
The new world. L2.
What the agents do, step by step:
- 1.The Data Context & Catalog agent calls
blast_radius_analysisand shows impact.
- 1.The Autonomous Data-Conductor calls
request_governance_reviewand holds at L2.
- 1.The Data Access & Governance agent calls
generate_audit_reportand records approval.
In practice. Approved.
What to measure. Changes with approver.
Designing the autonomy ladder
Autonomy is set per task class, not per tool. This is where we would set each class for a mature deployment, and why:
| Task class | Closed autonomously | Escalated | Handled by a person | Where we set it | Why |
|---|---|---|---|---|---|
| Catalog upkeep | 88% | 8% | 4% | L4 once the receipts are clean | The work is reversible and repeatable |
| Payer mapping | 66% | 24% | 10% | L3: acts and keeps a rollback point | Most cases are routine; the rest escalate with evidence |
| Registry refresh | 80% | 14% | 6% | L4 once the receipts are clean | The work is reversible and repeatable |
| Attribution checks | 62% | 28% | 10% | L3: acts and keeps a rollback point | Most cases are routine; the rest escalate with evidence |
| Settlement inputs | 0% | 86% | 14% | L2: always proposed to a named approver | The number carries accountability outside the data team |
The operating model: who owns what
Agents change who does the work, not who is accountable for it:
| Role | Owns | What the agents take off their plate |
|---|---|---|
| Director of Population Health Analytics | Standards, autonomy levels per domain and which domain goes next | Assembling status, chasing owners, keeping the catalog current |
| Domain owners and approvers | Settlement inputs and published scorecards | Preparing the diff, blast radius and rollback plan for every proposal |
| Data engineers | Reviewing agent proposals and building new data products | Payer files are mapped on arrival; registries refresh continuously |
The swarm behind the practices
| Agent | What it does for you | Tools it calls |
|---|---|---|
| Data Ingestion | Payer files, attribution lists and EHR extracts | get_connector_status, trigger_airflow_dag, register_kafka_schema |
| Schema Evolution | Payer layout changes | detect_schema_change, validate_schema_compatibility, generate_migration, rollback_migration |
| Pipeline Building | Registries, risk and contract models | generate_pipeline, validate_pipeline, sandbox_test, deploy_pipeline |
| Quality Monitoring | Attribution reconciliation and completeness | set_sla, run_quality_check, get_anomalies, create_quality_tests_for_pipeline |
| Data Context & Catalog | Governed contract and quality definitions | trace_cross_platform_lineage, blast_radius_analysis, define_business_rule, generate_documentation |
| Data Security | PHI classification | scan_pii, review_pii_writes, pci_card_data_masking |
Data Context Wizard keeps one governed graph of definitions, lineage and owners that every agent and person answers from. Autonomous Data-Conductor runs each job from detection to a verified result. Spellbook Data Catalog is where your team approves, audits and rolls back, and asks questions in plain English.
What disappears
- •Lost months after payer changes.
- •Attribution disputes.
- •Stale gap lists.
- •Settlement surprises.
- •Hand-built registries.
The magic is not any single agent. It is that the back office keeps running: bad data is caught where it enters, every new table gets quality rules and documentation without anyone writing them, access follows policy, fixes are verified before anyone opens a dashboard, and every action leaves a signed receipt.
A product manager's scorecard
| Metric | How to read it |
|---|---|
| Months without reports | Baseline it in the first week of the pilot; review it monthly. |
| Attribution disputes | Baseline it in the first week of the pilot; review it monthly. |
| List age | Baseline it in the first week of the pilot; review it monthly. |
| Conflicting metrics | Baseline it in the first week of the pilot; review it monthly. |
| Changes with approver | Baseline it in the first week of the pilot; review it monthly. |
Where this goes next
Population health teams will manage every value-based contract on current data, with registries and contract performance refreshed continuously and settlement holding no surprises.
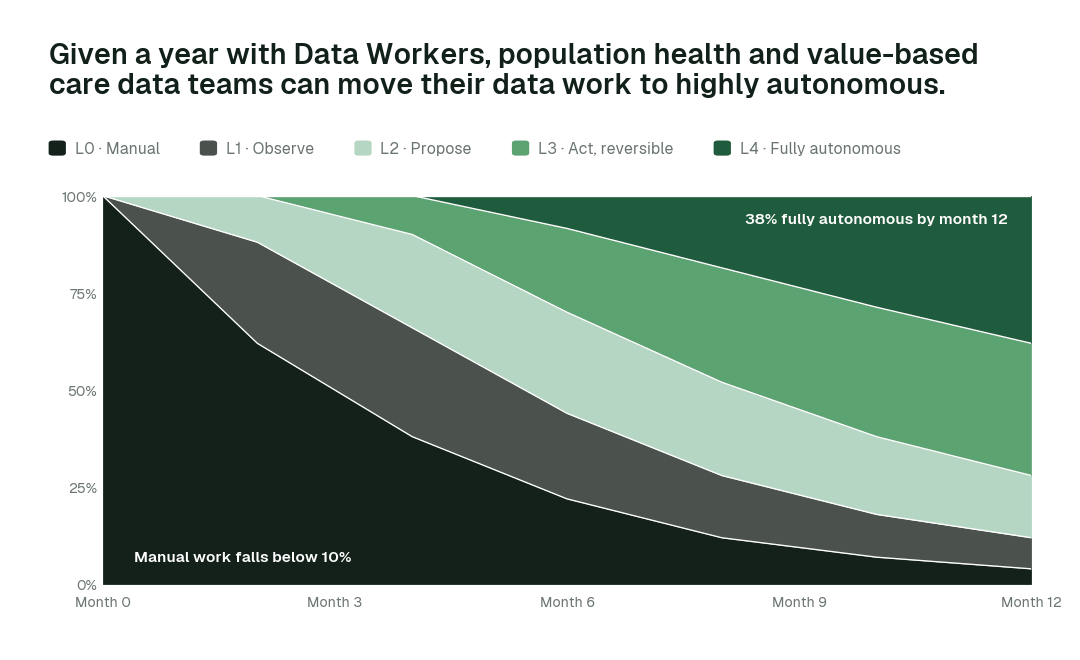
The climb: from assisted to autonomous to agentic
Our thesis is that the data platform climbs the way analytics did, in stages, and that the hard part of data work was never knowing what to do but doing it. For population health and value-based care data teams, the climb looks like this:
- •Assisted. Agents work alongside your team. They read the whole stack, show what needs doing and propose every fix with a receipt; settlement inputs and published scorecards always go to a named approver.
- •Autonomous, under your governance. Routine work runs on its own: payer files are mapped on arrival, registries refresh continuously, and attribution reconciles monthly. Your team governs the agents instead of doing the upkeep.
- •The agentic enterprise. Population health teams will manage every value-based contract on current data, with registries and contract performance refreshed continuously and settlement holding no surprises.
You choose the altitude, every step is visible and reversible, and the pilot below is the first rung.
The pilot: how population health and value-based care data teams start
The pilot is how your team proves the value on its own data before committing.
- •What we connect. Epic Healthy Planet or other population health tools; payer claims and attribution files; Databricks or Snowflake; dbt; BI, over MCP, inside your infrastructure. Nothing migrates.
- •Scope. Two payer contracts at L2.
- •First week. Agents run at L1 across the scoped domain. They map every pipeline, definition and lineage path and show the fixes they would have made, with receipts, so your team sees the value before anything changes.
- •By week two. Payer files are mapped on arrival and registries refresh continuously start running on reversible work. Settlement inputs and published scorecards stay at L2 with a named approver.
- •At day 30. We review the impact metrics against your baseline:
- Gap flagged: from about 2 weeks to ~1 h
- Payer file mapped: from about a week to ~1 h
- Attribution reconciled: from about a week to 2 h
- the share of catalog upkeep closed autonomously, targeting 88% as the deployment matures
- •What you decide. Whether to expand to the next domain. The pilot fee is credited in full against the first year.
- •Cost. Start with a pilot ($7,500 one-time, credited in full against the first year). Scale is from $1,000 a month and Enterprise from $3,000 a month, billed annually, with unlimited seats, no usage meter and no markup on model spend. See pricing.
The pilot is the start of a longer curve:
Read the full playbook: Data Workers for population health and value-based care data teams