Agentic population health and value-based care data: a guide for population health and value-based care data teams
This guide explains how population health and value-based care data teams adopt agents for their data back office. It covers the shift underway, the use cases that matter most, charts of the impact, how the agents work together, and a month-by-month path to autonomy.
Key takeaways
- •Who this is for. Teams that run attribution, registries, risk scores, quality gaps and contract performance for value-based arrangements.
- •The problem today. Payer files mapped by hand every month, disputed attribution and gap lists that are a month old.
- •What changes. Payer files are mapped on arrival, so reports never stop for a layout change. Registries refresh continuously, so care managers work from current lists.
- •What stays with your people. Settlement inputs and published scorecards: money moves on them, so the population health lead approves.
- •The result. Population health teams that manage contracts monthly and reach patients while it matters.
The PRD for agentic population health and value-based care data teams
This is the requirements document we would write with you for your team. Everything below expands on it.
| Who | Population health, value-based care, ACO and care management analytics teams at health systems, provider groups and payers |
| The job | Attribution, registries and contract performance current every month. |
| Environment | Epic Healthy Planet or other population health tools; payer claims and attribution files; Databricks or Snowflake; dbt; BI. |
| Constraints | Settlement inputs and published scorecards always go to a named approver. Population health data is PHI shared under payer agreements. |
| Success is measured by | Gap flagged: from about 2 weeks to ~1 h; Payer file mapped: from about a week to ~1 h; Attribution reconciled: from about a week to 2 h; catalog upkeep closed autonomously 88% of the time. |
| Owned by | A Director of Population Health Analytics, with domain owners as named approvers. |
| Pilot scope | Two payer contracts at L2. |
What going fully agentic and autonomous means for population health and value-based care data teams
- •Put your data pipeline on autopilot. Payer files are mapped on arrival, so reports never stop for a layout change.
- •Run the data back office without the busywork. The work that fills the week today moves to agents: payer files mapped by hand every month, disputed attribution and gap lists that are a month old.
- •Scale data without scaling headcount. Registries refresh continuously and attribution reconciles monthly, so the data you manage grows without the team having to.
- •Get the plumbing off your plate. Population health teams that manage contracts monthly and reach patients while it matters.
Who this is for
Teams that run attribution, registries, risk scores, quality gaps and contract performance for value-based arrangements. They combine EHR data with payer claims files, attribution lists and social data, and serve care management, finance and contracting.
The shift
Value-based contracts pay for outcomes, but the data to manage them arrives late from payers in formats that change every month. Teams spend most of their time making files usable. Agents can land, map and reconcile payer data continuously, so care teams act on current lists and contract performance is visible before settlement.
The product you ship
- •Attribution and panel data
- •Registries and risk scores
- •Quality gap lists
- •Contract performance and shared-savings tracking
Where the week goes
- •Payer files change layout monthly.
- •Attribution lists disagree with the EHR.
- •Registries are rebuilt by hand.
- •Risk scores lag.
- •Settlement surprises arrive a year later.
Add it up and upkeep is most of the team's week. Here is how a typical week splits today, and once agents own the back office:
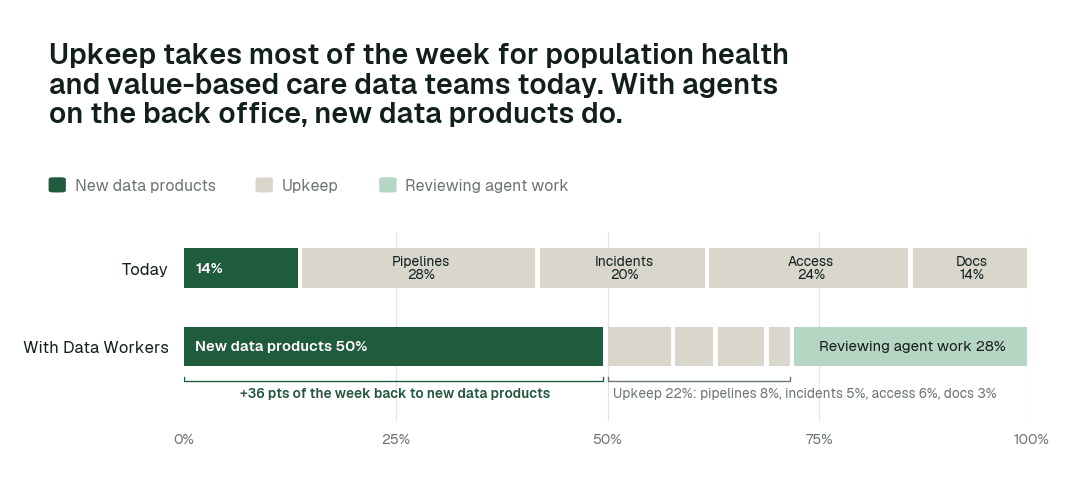
Time spent on new data products moves from 14% of the week to 50%. Most of the rest becomes review: people steer and approve agent work instead of doing it by hand.
Then and now
| Work | Today | With Data Workers |
|---|---|---|
| Payer files | Mapped by hand | Mapped on arrival |
| Attribution | Disputed | Reconciled monthly |
| Registries | Monthly rebuilds | Continuous |
| Quality gaps | Found late | Flagged as data lands |
| Contract performance | At settlement | Monthly |
These are the impact metrics we move for population health and value-based care data teams:
- •Gap flagged: from about 2 weeks to ~1 h
- •Payer file mapped: from about a week to ~1 h
- •Attribution reconciled: from about a week to 2 h
Across the routine work in this domain:
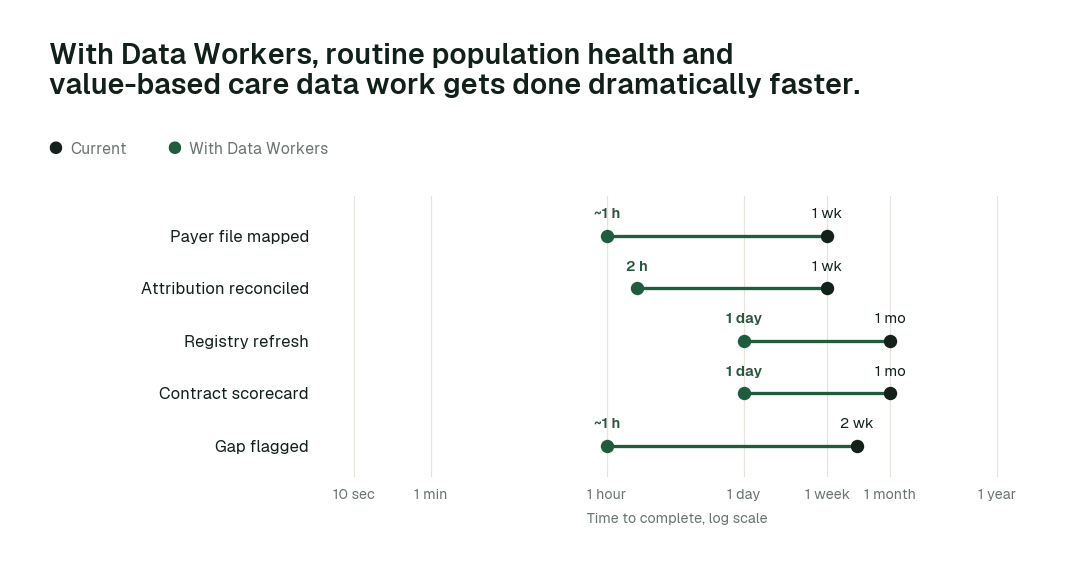
The biggest change is Gap flagged: from about 2 weeks to ~1 h.
Use cases, in depth
A payer file in a new layout
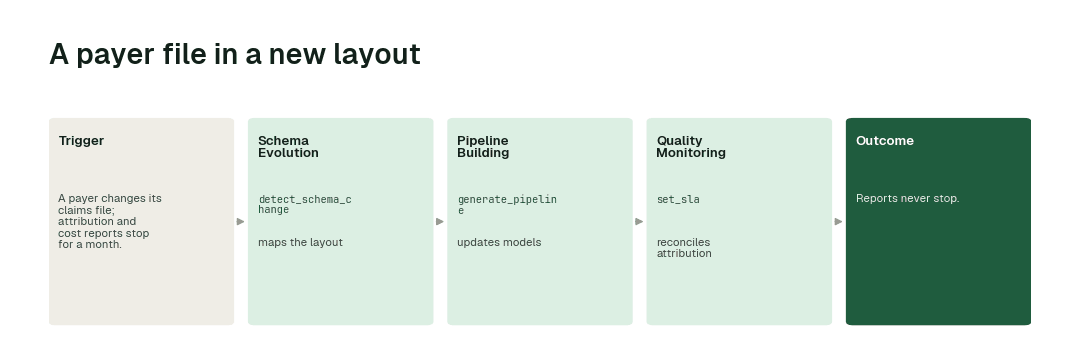
Today. A payer changes its claims file; attribution and cost reports stop for a month.
With Data Workers. Schema Evolution maps the layout, Pipeline Building updates models, Quality Monitoring reconciles attribution.
What changes. Reports never stop.
Care gaps closed in time
Today. Gap lists are a month old when care managers get them.
With Data Workers. Registries refresh continuously and gaps are flagged as data lands.
What changes. Outreach reaches patients while it matters.
Contract performance before settlement
Today. Shared savings are a surprise a year later.
With Data Workers. Agents compute contract metrics monthly from governed definitions.
What changes. Leaders manage the contract, not the surprise.
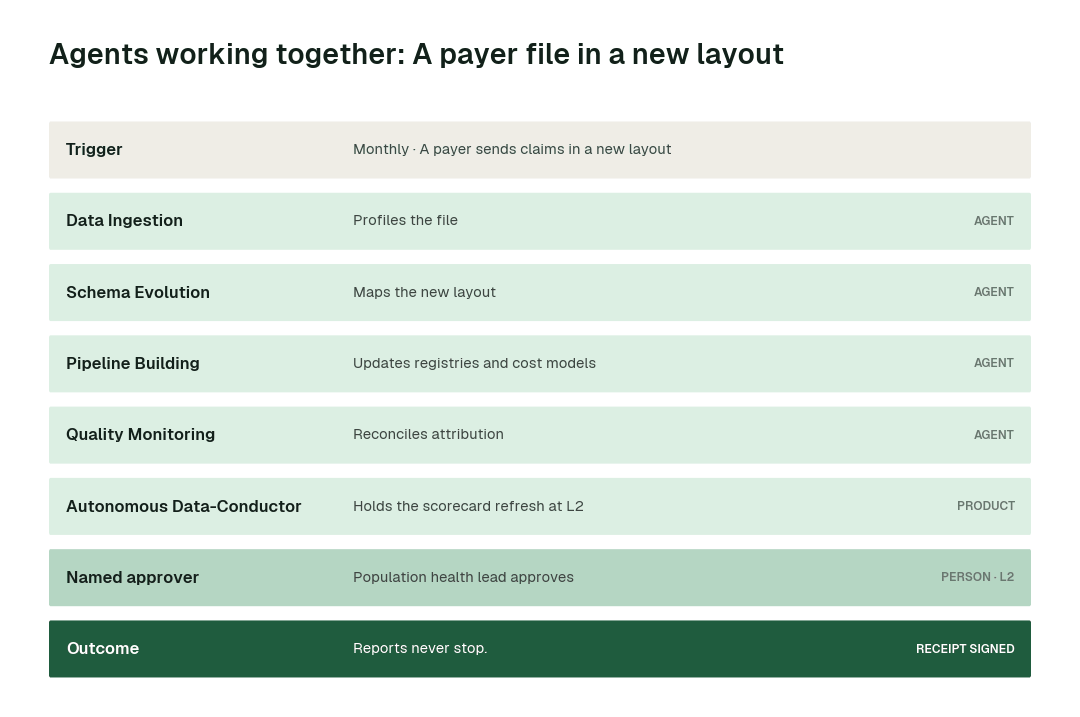
Agents working together: A payer file in a new layout
Minute by minute
Illustrative example. Payer files land monthly in Databricks; registries refresh nightly.
| Time | Who | What happens |
|---|---|---|
| Day 3 | Payer | Claims file in new layout |
| Day 3 | Data Ingestion agent | Profiled; layout change found |
| Day 3 | Schema Evolution agent | Mapped |
| Day 3 | Quality Monitoring agent | Attribution reconciled |
| Day 4 | Spellbook Data Catalog | Lead approves scorecard refresh |
The agents on the job
| Agent | What it does for you | Tools it calls |
|---|---|---|
| Data Ingestion | Payer files, attribution lists and EHR extracts | get_connector_status, trigger_airflow_dag, register_kafka_schema |
| Schema Evolution | Payer layout changes | detect_schema_change, validate_schema_compatibility, generate_migration, rollback_migration |
| Pipeline Building | Registries, risk and contract models | generate_pipeline, validate_pipeline, sandbox_test, deploy_pipeline |
| Quality Monitoring | Attribution reconciliation and completeness | set_sla, run_quality_check, get_anomalies, create_quality_tests_for_pipeline |
| Data Context & Catalog | Governed contract and quality definitions | trace_cross_platform_lineage, blast_radius_analysis, define_business_rule, generate_documentation |
| Data Security | PHI classification | scan_pii, review_pii_writes, pci_card_data_masking |
Data Context Wizard keeps one governed graph of definitions, lineage and owners that every agent and person answers from. Autonomous Data-Conductor runs each job from detection to a verified result. Spellbook Data Catalog is where your team approves, audits and rolls back, and asks questions in plain English.
What goes on autopilot
Once a domain has earned it, this work runs on its own, and each item removes a problem your team deals with today:
- •Payer files are mapped on arrival, so reports never stop for a layout change.
- •Registries refresh continuously, so care managers work from current lists.
- •Attribution reconciles monthly, so panels are agreed.
Where your people stay in charge
Agents never get blanket access. Each domain has its own autonomy level, set by you, and it only rises when the receipts show the agents are reliable. Everything starts at L1, observing only; reversible upkeep such as reruns, staging fixes, documentation and cleanup is usually first to run on its own.
- •Settlement inputs and published scorecards always goes to a named approver: money moves on them, so the population health lead approves.
- •Contract and care decisions: these stay with people.
Once a deployment has matured, here is how that ladder plays out across task classes:
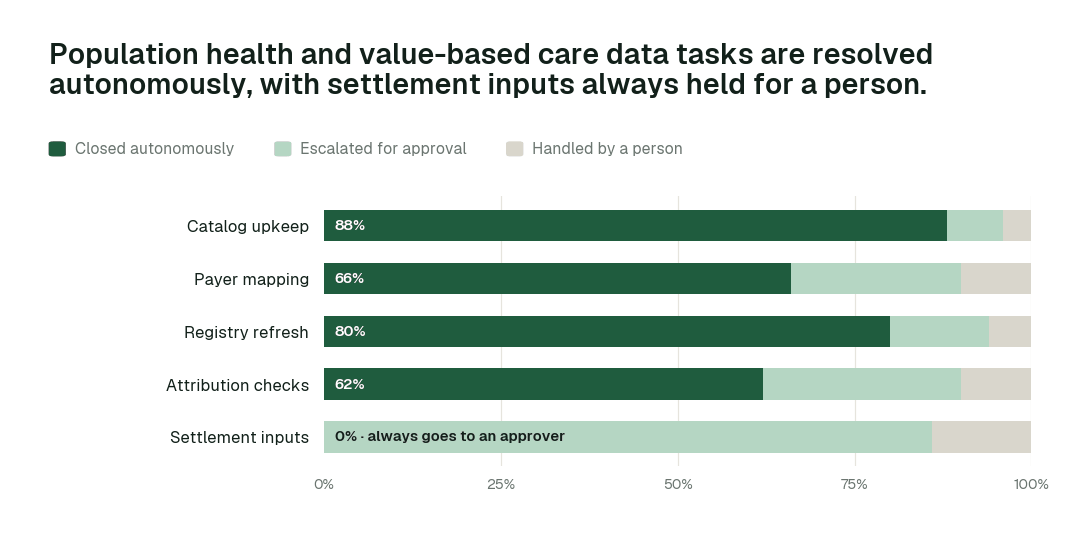
Catalog upkeep closes autonomously 88% of the time. For Settlement inputs, autonomous closure is 0% by design.
What happens when an agent is wrong
- •At L2 propose, nothing changes until a named person approves. The proposal shows the full diff, the blast radius and how to roll it back. Unanswered requests expire and escalate.
- •At L3 act, reversibly, every change keeps a rollback point, and Conductor verifies the downstream number after the change. If verification fails, the change is reversed and the domain drops a level.
- •No agent approves or promotes its own work. Autonomy only grows on evidence, per repair class, and repeated errors shrink scope automatically.
- •One org-wide stop halts all autonomous dispatch, and every action lands in a hash-chained audit trail you can export with generate_audit_report.
How it fits your stack
Data Workers connects to what you already run: Epic Healthy Planet or other population health tools; payer claims and attribution files; Databricks or Snowflake; dbt; BI. Each agent is an MCP server, so the same agents work inside Claude Code, Cursor or Codex and in Slack or Teams through Spellbook. Nothing migrates.
- •Runs in your infrastructure with your credentials and your model key. The hosted Autonomous Data-Conductor sees workflow metadata only, never rows.
- •Uses the access you already govern. Agents act under scoped service identities and your existing roles; every grant goes through provision_access and is logged.
- •Proposes changes as diffs in your dbt project, orchestrator and warehouse, with blast radius, tests and a rollback point, and applies them only at the autonomy level you set for that domain.
- •Open-source core. The Apache-2.0 community edition ships 11 agents and 160+ MCP tools, so your engineers can read exactly what the agents call.
Governance and regulation
Population health data is PHI shared under payer agreements. Data Workers classifies PHI, enforces data-use terms and logs access.
Data Workers doesn't make you compliant; your controls, people and assessors do. It supplies controls and evidence wherever agents touch data. Not legal advice.
The alternatives population health and value-based care data teams weigh
Build it yourselves. A strong team can wire a coding agent to MCP servers for the warehouse and dbt. The work is everything around it: routing approvals to the right owner, blast radius, rollback, receipts, and current context about every other system.
Observability, catalogs and point tools. Observability alerts, catalogs document, and quality tools test. Data Workers takes their signals, diagnoses, proposes the fix, verifies it and leaves the receipt.
Platform-native agents. Snowflake made its managed MCP server and Cortex Agents generally available on Nov 4, 2025, and Databricks made Genie One generally available on Jun 16, 2026. They are excellent inside their platform; this work crosses the source systems, orchestrator, warehouse and BI, and Data Workers works across all of them.
In this space specifically. Population health platforms run care workflows; Data Workers keeps the data under them current and reconciled.
The case for your CTO
What this replaces. Payer files mapped by hand every month, disputed attribution and gap lists that are a month old.
What your team gets back. Population health teams that manage contracts monthly and reach patients while it matters.
Integration effort. Connecting is configuration, not a migration. The agents attach over MCP to the warehouse, orchestrator, dbt project and source systems you already run, under the roles you already govern, inside your own infrastructure. Your engineers can read every tool the agents call in the open-source core.
Risk and control. Autonomy is set per domain. Everything starts at L1, observing only; reversible work moves up only when the receipts justify it; settlement inputs and published scorecards stay at L2 with a named approver; and one org-wide stop halts all autonomous work.
Why now. Value-based revenue is growing.
The first win. Two payer contracts at L2. The pilot below lays out the scope, what you see each week and the cost.
The climb: from assisted to autonomous to agentic
Our thesis is that the data platform climbs the way analytics did, in stages, and that the hard part of data work was never knowing what to do but doing it. For population health and value-based care data teams, the climb looks like this:
- •Assisted. Agents work alongside your team. They read the whole stack, show what needs doing and propose every fix with a receipt; settlement inputs and published scorecards always go to a named approver.
- •Autonomous, under your governance. Routine work runs on its own: payer files are mapped on arrival, registries refresh continuously, and attribution reconciles monthly. Your team governs the agents instead of doing the upkeep.
- •The agentic enterprise. Population health teams will manage every value-based contract on current data, with registries and contract performance refreshed continuously and settlement holding no surprises.
You choose the altitude, every step is visible and reversible, and the pilot below is the first rung.
The pilot: how population health and value-based care data teams start
The pilot is how your team proves the value on its own data before committing.
- •What we connect. Epic Healthy Planet or other population health tools; payer claims and attribution files; Databricks or Snowflake; dbt; BI, over MCP, inside your infrastructure. Nothing migrates.
- •Scope. Two payer contracts at L2.
- •First week. Agents run at L1 across the scoped domain. They map every pipeline, definition and lineage path and show the fixes they would have made, with receipts, so your team sees the value before anything changes.
- •By week two. Payer files are mapped on arrival and registries refresh continuously start running on reversible work. Settlement inputs and published scorecards stay at L2 with a named approver.
- •At day 30. We review the impact metrics against your baseline:
- Gap flagged: from about 2 weeks to ~1 h
- Payer file mapped: from about a week to ~1 h
- Attribution reconciled: from about a week to 2 h
- the share of catalog upkeep closed autonomously, targeting 88% as the deployment matures
- •What you decide. Whether to expand to the next domain. The pilot fee is credited in full against the first year.
- •Cost. Start with a pilot ($7,500 one-time, credited in full against the first year). Scale is from $1,000 a month and Enterprise from $3,000 a month, billed annually, with unlimited seats, no usage meter and no markup on model spend. See pricing.
The pilot is the start of a longer curve:
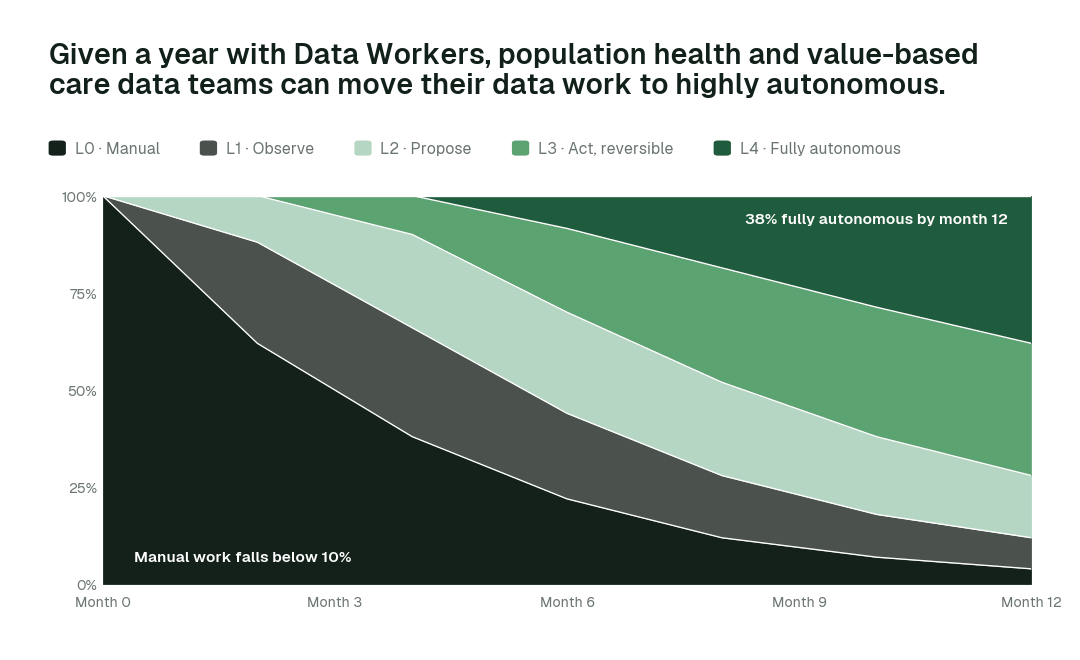
By month 12, more than 38% of agent actions run fully autonomously while settlement inputs stay with a named approver.
FAQ
Does it replace our population health platform? No; it keeps its data current.
Who approves scorecards? A named lead.
PHI? Stays in your environment.
Where do the agents run? In your infrastructure, with your credentials and model key. The hosted Conductor sees workflow metadata only.
Do we have to migrate anything? No. Your warehouse, dbt project, orchestrator, catalog and BI stay where they are.
Sources
- •Data Workers pricing: https://dataworkers.io/pricing/
- •Snowflake, managed MCP server and Cortex Agents GA release note (Nov 4, 2025): https://docs.snowflake.com/en/release-notes/2025/other/2025-11-04-cortex-agents-mcp
- •Databricks, Genie One launch (Jun 16, 2026): https://www.databricks.com/company/newsroom/press-releases/databricks-launches-genie-one-all-new-agentic-coworker-every-team